Very few pathologists specialise in the lung, fewer still in interstitial disease.
Neolung is built so that what they know reaches every lung report: what a specialist looks for in the tumour and in the lung around it, checked before the report is signed, starting from what you dictate. For every hospital without a lung specialist down the corridor, and every trainee learning to.
When I retire, there will be four of us left in the world.
Dr M. Ángeles Montero-Fernández Neolung's clinical lead, on how few pathologists specialise in interstitial lung disease, as she sees it.
She has spent 36 years in histopathology, 22 of them in thoracic pathology: tumours, interstitial disease and transplants. The report types in Neolung are written in her words.
Fellowship in lung pathology, Mayo Clinic, Arizona
2004 Thoracic pathologist, Vall d'Hebron, Barcelona
2012 Consultant, Royal Brompton, London
2018 Consultant and, from 2020, Clinical Director, Manchester University NHS Foundation Trust, a referral centre for interstitial disease and transplantation
2019 Steering committee, British Thoracic Oncology Group
2024 Senior consultant, Liverpool Clinical Laboratories
Institutions are named as her career; they don't endorse Neolung.
Neolung for pathologists and for hospitals
For pathologists
Your eyes and your judgement. Not your typing.
You look, you decide, you say it. Neolung fills a specialist's template from it, checks it, and waits for your signature.
Say it once
The diagnosis in a line, by voice or typed. The report is filled from what you said; anything you didn't say stays empty for you to add.
Checked before you sign
What's missing and what contradicts, against RCPath, ICCR and TNM, each warning with its guideline.
The lung around the tumour
Report types that ask for the background lung and interstitial disease, in a specialist's words.
Fourteen report types, in a specialist's words
From a lung resection to a transplant biopsy. Choose one to see what it asks for, what it checks, and how you'd dictate it.
Lung cancer
Lung resection (primary carcinoma)
Resection for primary lung carcinoma, written as the clinical lead reports it.
sections
6
fields
37
checks
12
The AI may suggest from photos: Histological type, Predominant pattern.
Written against: UICC TNM Classification of Malignant Tumours, 9th edition: lung; RCPath dataset for histopathological reporting of lung cancer; ICCR dataset: lung cancer, resection.
Dictate it like this
Right upper lobe resection. Non-mucinous adenocarcinoma, papillary 75%, lepidic 25%, 17 mm. PL0, away from the stapled line. Margins and hilar nodes clear. Stations 11R, 4R, 2R and 7 clear. Background lung unremarkable. pT1b N0 R0.Right upper lobe resection. Non-mucinous adenocarcinoma, papillary 75%, lepidic 25%, 17 mm. PL0, away from the stapled line. Margins and hilar nodes clear. Stations 11R, 4R, 2R and 7 clear. Background lung unremarkable. pT1b N0 R0.Right upper lobe resection. Non-mucinous adenocarcinoma, papillary 75%, lepidic 25%, 17 mm. PL0, away from the stapled line. Margins and hilar nodes clear. Stations 11R, 4R, 2R and 7 clear. Background lung unremarkable. pT1b N0 R0.
Specimen2 fields
Tumour18 fields
Margins2 fields
Lymph nodes8 fields
Non-neoplastic lung3 fields
Pathological stage4 fields
Lung cancer
Lung resection, metastasis
Wedge or lobectomy for a metastasis (colorectal, ovarian, renal, sarcoma), written as the clinical lead reports it. For a primary lung carcinoma, use the lung resection.
sections
2
fields
15
checks
9
Written against: The clinical lead's own reports.
Dictate it like this
Right lower lobe wedge. Sections show an adenocarcinoma entirely consistent with a colorectal primary. Tumour is away from the visceral pleura and the stapled line. Background lung is unremarkable. Diagnosis: adenocarcinoma consistent with colorectal primary, completely resected.Right lower lobe wedge. Sections show an adenocarcinoma entirely consistent with a colorectal primary. Tumour is away from the visceral pleura and the stapled line. Background lung is unremarkable. Diagnosis: adenocarcinoma consistent with colorectal primary, completely resected.Right lower lobe wedge. Sections show an adenocarcinoma entirely consistent with a colorectal primary. Tumour is away from the visceral pleura and the stapled line. Background lung is unremarkable. Diagnosis: adenocarcinoma consistent with colorectal primary, completely resected.
Microscopy9 fields
Diagnosis6 fields
Lung cancer
Lung biopsy (small)
Needle core, bronchial or EBUS biopsy for suspected carcinoma, written as the clinical lead reports it.
sections
10
fields
61
checks
19
Written against: The clinical lead's own reports.
Dictate it like this
Lung biopsy, right upper lobe. Two needle core biopsies with extensive infiltration by a non-mucinous adenocarcinoma, acinar and lepidic patterns. Block for molecular tests A1, tumour 40%, no necrosis.Lung biopsy, right upper lobe. Two needle core biopsies with extensive infiltration by a non-mucinous adenocarcinoma, acinar and lepidic patterns. Block for molecular tests A1, tumour 40%, no necrosis.Lung biopsy, right upper lobe. Two needle core biopsies with extensive infiltration by a non-mucinous adenocarcinoma, acinar and lepidic patterns. Block for molecular tests A1, tumour 40%, no necrosis.
Specimen3 fields
EBUS sample A7 fields
EBUS sample B7 fields
EBUS sample C7 fields
EBUS sample D7 fields
EBUS sample E7 fields
EBUS sample F7 fields
Findings12 fields
Molecular testing3 fields
Comment1 fields
Other lung
Lung biopsy, non-neoplastic
Lung biopsy without a tumour: granulomas, amyloid, acute lung injury, organising pneumonia, hamartoma. For a carcinoma, carcinoid or metastasis, use the small lung biopsy.
sections
2
fields
15
checks
9
Written against: The clinical lead's own reports.
Dictate it like this
Lung biopsy, left lower lobe. The alveolar septa are thickened with neutrophils and eosinophils, with fibrin and focal organisation. No vasculitis, capillaritis or criteria of a specific infection. Diagnosis: acute lung injury with focal organising areas. Special stains to follow.Lung biopsy, left lower lobe. The alveolar septa are thickened with neutrophils and eosinophils, with fibrin and focal organisation. No vasculitis, capillaritis or criteria of a specific infection. Diagnosis: acute lung injury with focal organising areas. Special stains to follow.Lung biopsy, left lower lobe. The alveolar septa are thickened with neutrophils and eosinophils, with fibrin and focal organisation. No vasculitis, capillaritis or criteria of a specific infection. Diagnosis: acute lung injury with focal organising areas. Special stains to follow.
Microscopy9 fields
Diagnosis6 fields
Other lung
Lung resection, non-neoplastic
Lobectomy or wedge without a tumour: bronchiectasis, fibroelastosis, completion lobectomy, written as the clinical lead reports it.
sections
2
fields
15
checks
9
Written against: The clinical lead's own reports.
Dictate it like this
Right upper lobe. The sections show a bronchiectasis with a thick fibrotic capsule, extending to the pleura with adhesions. The bronchial and vascular resection margins and the lymph nodes are unremarkable. No malignancy seen. Diagnosis: bronchiectasis, fibrosis and inflammation.Right upper lobe. The sections show a bronchiectasis with a thick fibrotic capsule, extending to the pleura with adhesions. The bronchial and vascular resection margins and the lymph nodes are unremarkable. No malignancy seen. Diagnosis: bronchiectasis, fibrosis and inflammation.Right upper lobe. The sections show a bronchiectasis with a thick fibrotic capsule, extending to the pleura with adhesions. The bronchial and vascular resection margins and the lymph nodes are unremarkable. No malignancy seen. Diagnosis: bronchiectasis, fibrosis and inflammation.
Microscopy9 fields
Diagnosis6 fields
Interstitial lung disease
Interstitial lung disease biopsy
Surgical, cryo or transbronchial biopsy for interstitial lung disease, written as the clinical lead reports it, with radiological correlation.
sections
4
fields
22
checks
3
Written against: The clinical lead's own reports; ATS/ERS/JRS/ALAT clinical practice guideline: diagnosis of idiopathic pulmonary fibrosis.
Dictate it like this
Surgical biopsy, right upper, middle and lower lobes, parts A and B. Sections from the three lobes show similar features. Patchy subpleural fibrosis with organising pneumonia within severe emphysema. Constrictive bronchiolitis as a sign of small airways disease. No granuloma formation is seen. Diagnosis: constrictive bronchiolitis within severe emphysema. Comment: connective tissue disease and micro-aspiration should be excluded.Surgical biopsy, right upper, middle and lower lobes, parts A and B. Sections from the three lobes show similar features. Patchy subpleural fibrosis with organising pneumonia within severe emphysema. Constrictive bronchiolitis as a sign of small airways disease. No granuloma formation is seen. Diagnosis: constrictive bronchiolitis within severe emphysema. Comment: connective tissue disease and micro-aspiration should be excluded.Surgical biopsy, right upper, middle and lower lobes, parts A and B. Sections from the three lobes show similar features. Patchy subpleural fibrosis with organising pneumonia within severe emphysema. Constrictive bronchiolitis as a sign of small airways disease. No granuloma formation is seen. Diagnosis: constrictive bronchiolitis within severe emphysema. Comment: connective tissue disease and micro-aspiration should be excluded.
Specimen2 fields
Findings14 fields
Radiological correlation3 fields
Conclusion3 fields
Transplant
Lung transplant biopsy
Transbronchial biopsy after lung transplant, written as the clinical lead reports it, with ISHLT grades.
sections
4
fields
23
checks
5
Written against: The clinical lead's own reports; ISHLT revised working formulation for the grading of lung allograft rejection.
Dictate it like this
Transplant TBB, right lower and middle lobe. Eight pieces, bronchial wall and alveolar interstitium. Two bronchioles show lymphocytic inflammation. Perivascular lymphocytic cuffing in the alveolar parenchyma. Mild acute cellular rejection and lymphocytic bronchiolitis, A2 B1R C0. DSA recommended.Transplant TBB, right lower and middle lobe. Eight pieces, bronchial wall and alveolar interstitium. Two bronchioles show lymphocytic inflammation. Perivascular lymphocytic cuffing in the alveolar parenchyma. Mild acute cellular rejection and lymphocytic bronchiolitis, A2 B1R C0. DSA recommended.Transplant TBB, right lower and middle lobe. Eight pieces, bronchial wall and alveolar interstitium. Two bronchioles show lymphocytic inflammation. Perivascular lymphocytic cuffing in the alveolar parenchyma. Mild acute cellular rejection and lymphocytic bronchiolitis, A2 B1R C0. DSA recommended.
Specimen5 fields
Findings7 fields
Rejection grades4 fields
Conclusion7 fields
Transplant
Lung explant
Native lungs removed at transplant, written as the clinical lead reports them.
sections
3
fields
19
checks
3
Written against: The clinical lead's own reports; ATS/ERS/JRS/ALAT clinical practice guideline: diagnosis of idiopathic pulmonary fibrosis.
Dictate it like this
Bilateral lung transplantation. Sections from both lungs show diffuse and severe emphysema. Patchy acute lung injury and organising pneumonia are noted. There is no evidence of malignancy. Diagnosis: diffuse severe emphysema consistent with the clinical diagnosis of alpha-1 antitrypsin deficiency.Bilateral lung transplantation. Sections from both lungs show diffuse and severe emphysema. Patchy acute lung injury and organising pneumonia are noted. There is no evidence of malignancy. Diagnosis: diffuse severe emphysema consistent with the clinical diagnosis of alpha-1 antitrypsin deficiency.Bilateral lung transplantation. Sections from both lungs show diffuse and severe emphysema. Patchy acute lung injury and organising pneumonia are noted. There is no evidence of malignancy. Diagnosis: diffuse severe emphysema consistent with the clinical diagnosis of alpha-1 antitrypsin deficiency.
Specimen1 fields
Findings15 fields
Conclusion3 fields
Pleura
Pleural biopsy
Pleural biopsy, benign or malignant, written as the clinical lead reports it.
sections
2
fields
17
checks
9
Written against: The clinical lead's own reports.
Dictate it like this
A and B. Sections show superficial pieces of pleura with marked mesothelial hyperplasia and lymphocytic inflammation. There is no granuloma formation or evidence of malignancy seen. Diagnosis: A and B, pleural biopsy, reactive mesothelial hyperplasia. Special stains to follow.A and B. Sections show superficial pieces of pleura with marked mesothelial hyperplasia and lymphocytic inflammation. There is no granuloma formation or evidence of malignancy seen. Diagnosis: A and B, pleural biopsy, reactive mesothelial hyperplasia. Special stains to follow.A and B. Sections show superficial pieces of pleura with marked mesothelial hyperplasia and lymphocytic inflammation. There is no granuloma formation or evidence of malignancy seen. Diagnosis: A and B, pleural biopsy, reactive mesothelial hyperplasia. Special stains to follow.
Microscopy9 fields
Diagnosis8 fields
Pleura
Pneumothorax resection
Bullectomy, apical wedge or pleurectomy for pneumothorax, written as the clinical lead reports it.
sections
2
fields
15
checks
9
Written against: The clinical lead's own reports.
Dictate it like this
Sections from the lung show mild pleural fibrosis and subpleural bullae. No granuloma formation or malignancy seen. The sections from the pleura show mesothelial hyperplasia and mild fibrosis. The overall features are those of recurrent pneumothorax.Sections from the lung show mild pleural fibrosis and subpleural bullae. No granuloma formation or malignancy seen. The sections from the pleura show mesothelial hyperplasia and mild fibrosis. The overall features are those of recurrent pneumothorax.Sections from the lung show mild pleural fibrosis and subpleural bullae. No granuloma formation or malignancy seen. The sections from the pleura show mesothelial hyperplasia and mild fibrosis. The overall features are those of recurrent pneumothorax.
Microscopy9 fields
Diagnosis6 fields
Pleura
Lung abscess and empyema
Lung abscess, empyema or decortication, written as the clinical lead reports it.
sections
2
fields
15
checks
9
Written against: The clinical lead's own reports.
Dictate it like this
A and B. Sections show a fibrinoid and organising pleuritis, with a fibrotic wall, superficial fibrin, granulation tissue and abundant mixed inflammation. There is no granuloma formation or malignancy seen. Diagnosis: A and B, abscess and pleural debris, fibrinoid and organising pleuritis and features consistent with empyema. Special stains in hand.A and B. Sections show a fibrinoid and organising pleuritis, with a fibrotic wall, superficial fibrin, granulation tissue and abundant mixed inflammation. There is no granuloma formation or malignancy seen. Diagnosis: A and B, abscess and pleural debris, fibrinoid and organising pleuritis and features consistent with empyema. Special stains in hand.A and B. Sections show a fibrinoid and organising pleuritis, with a fibrotic wall, superficial fibrin, granulation tissue and abundant mixed inflammation. There is no granuloma formation or malignancy seen. Diagnosis: A and B, abscess and pleural debris, fibrinoid and organising pleuritis and features consistent with empyema. Special stains in hand.
Microscopy9 fields
Diagnosis6 fields
Consultation
Referral opinion
An opinion on a case sent by a colleague, written as the clinical lead writes her letters.
sections
1
fields
12
checks
0
Written against: The clinical lead's own reports.
Dictate it like this
Thank you for sending me this interesting case. I agree with you that the features are those of a congenital pulmonary airway malformation, type 1. In the slides I have gone through the lesions are completely resected, however I would also advise follow up.Thank you for sending me this interesting case. I agree with you that the features are those of a congenital pulmonary airway malformation, type 1. In the slides I have gone through the lesions are completely resected, however I would also advise follow up.Thank you for sending me this interesting case. I agree with you that the features are those of a congenital pulmonary airway malformation, type 1. In the slides I have gone through the lesions are completely resected, however I would also advise follow up.
Letter12 fields
Cytology
Respiratory cytology
Bronchial washings, bronchoalveolar lavage or brushings, written as the clinical lead reports them.
sections
2
fields
15
checks
9
Written against: The clinical lead's own reports.
Dictate it like this
The slides show a hypercellular cytology with abundant bronchial cells and alveolar macrophages within a background of neutrophils. There is no granuloma formation or evidence of malignancy seen. Diagnosis: bronchial washings, acute inflammation. Comment: infection should be excluded in the first instance.The slides show a hypercellular cytology with abundant bronchial cells and alveolar macrophages within a background of neutrophils. There is no granuloma formation or evidence of malignancy seen. Diagnosis: bronchial washings, acute inflammation. Comment: infection should be excluded in the first instance.The slides show a hypercellular cytology with abundant bronchial cells and alveolar macrophages within a background of neutrophils. There is no granuloma formation or evidence of malignancy seen. Diagnosis: bronchial washings, acute inflammation. Comment: infection should be excluded in the first instance.
Microscopy9 fields
Diagnosis6 fields
Cytology
Pleural fluid cytology
Pleural fluid or effusion, smears and clot, written as the clinical lead reports it.
sections
2
fields
15
checks
9
Written against: The clinical lead's own reports.
Dictate it like this
The section from the blood clot shows abundant small lymphocytes and occasional mesothelial cells within a haematic background. There is no granuloma formation or evidence of malignancy seen. Diagnosis: pleural fluid, lymphocytic effusion.The section from the blood clot shows abundant small lymphocytes and occasional mesothelial cells within a haematic background. There is no granuloma formation or evidence of malignancy seen. Diagnosis: pleural fluid, lymphocytic effusion.The section from the blood clot shows abundant small lymphocytes and occasional mesothelial cells within a haematic background. There is no granuloma formation or evidence of malignancy seen. Diagnosis: pleural fluid, lymphocytic effusion.
Microscopy9 fields
Diagnosis6 fields
The case, as you'll review it
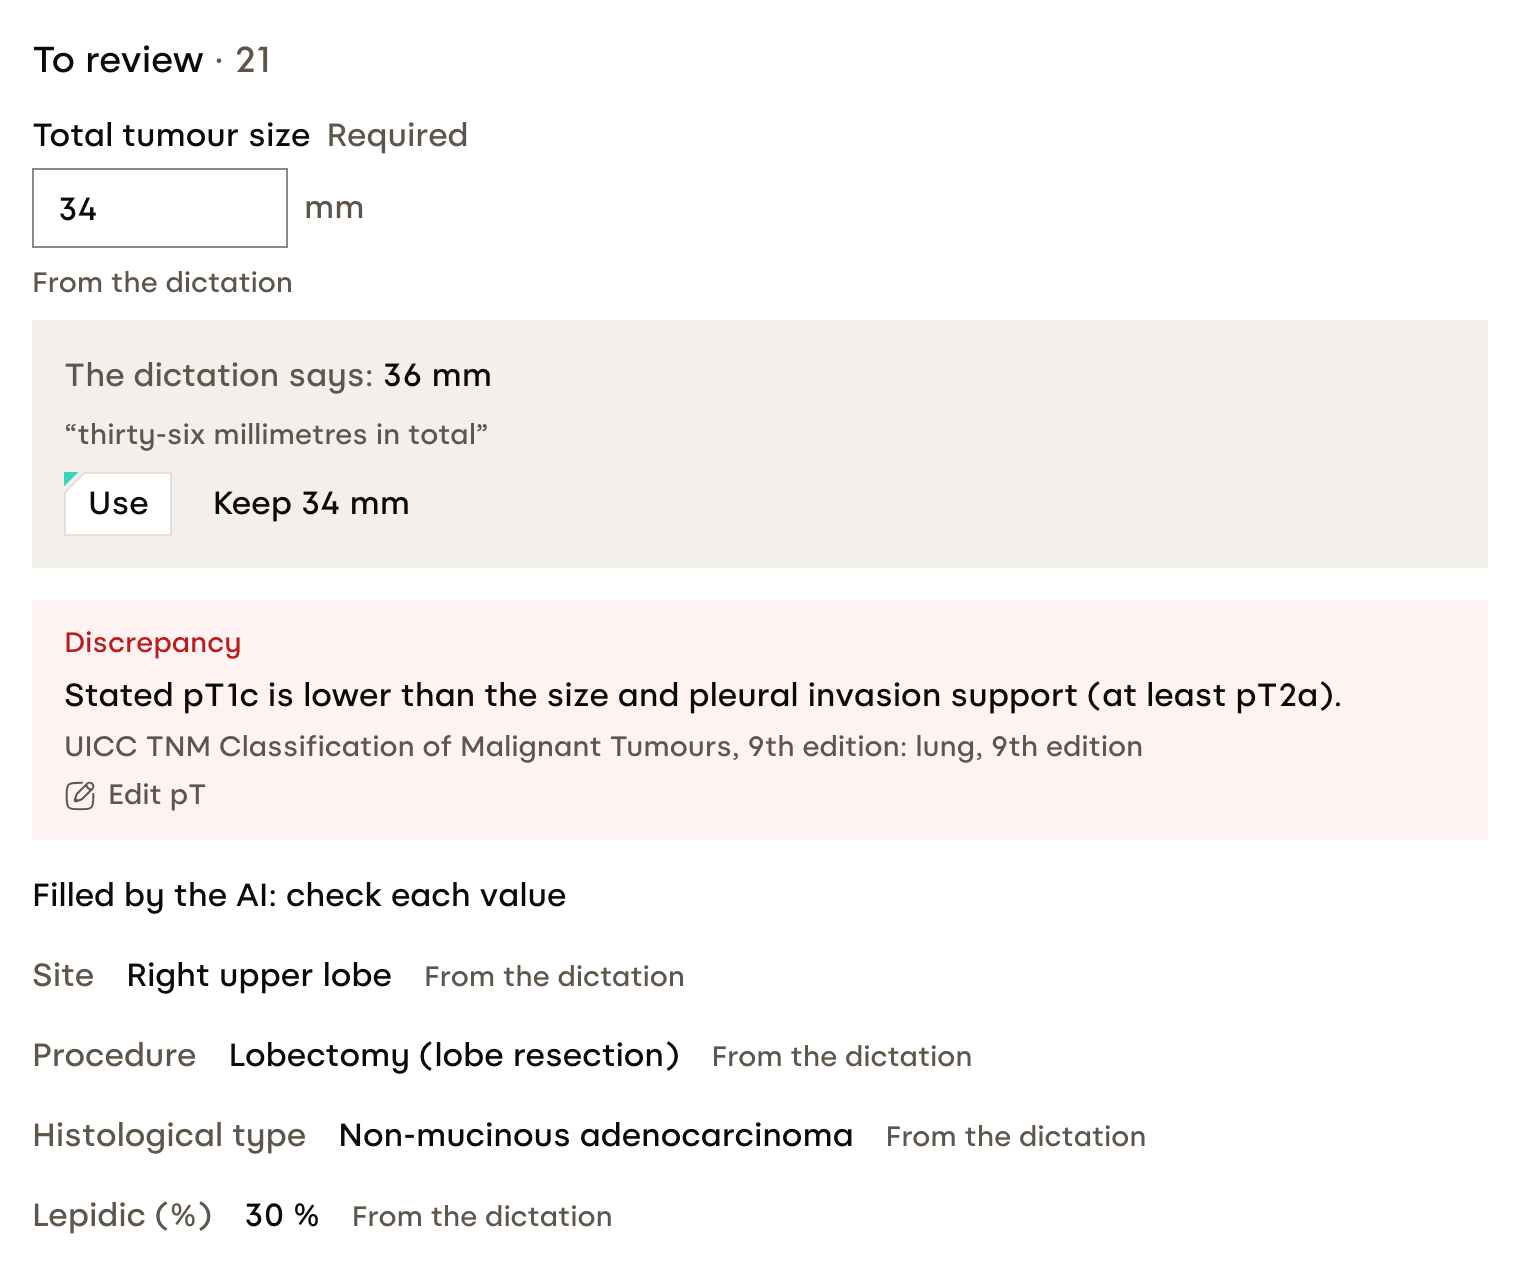
What the dictation filled is marked as such. Where you said a value differently later, you choose which to keep. A contradiction shows the guideline behind it, and how to settle it.
Small biopsies: the block for molecular tests
Record a carcinoma without the block for molecular tests, or a block without its tumour share, and Neolung points it out before you sign. A result that comes later goes in a supplementary report, alongside the signed one.
Record the block for molecular tests.
Record the tumour percentage in the block for molecular tests.
A sample shows carcinoma: record the block for molecular tests.
For trainees: every warning says why
Open a warning to see the guideline behind it. The same two the worked case raises, as Neolung writes them.
The same datasets, for every pathologist who reports.
The required items asked for every time, whoever writes the report. And a supplier that writes down how it protects your data and your patients.
Works alongside your laboratory system, from day one
No integration project, no install, no change to the laboratory system. Your pathologists open Neolung in a browser, report and sign, then paste the signed report where they paste reports today. An administrator sets your department up; IT isn't needed.
Neolungin the browser
Signed
Copy, paste
Your laboratory systemas it is today
What you don't need
An integration project
Software installed by IT
Any change to the laboratory system
What you have from the first day
Your department, set up by an administrator
The documentation your governance asks for
All your data, to export whenever you want it
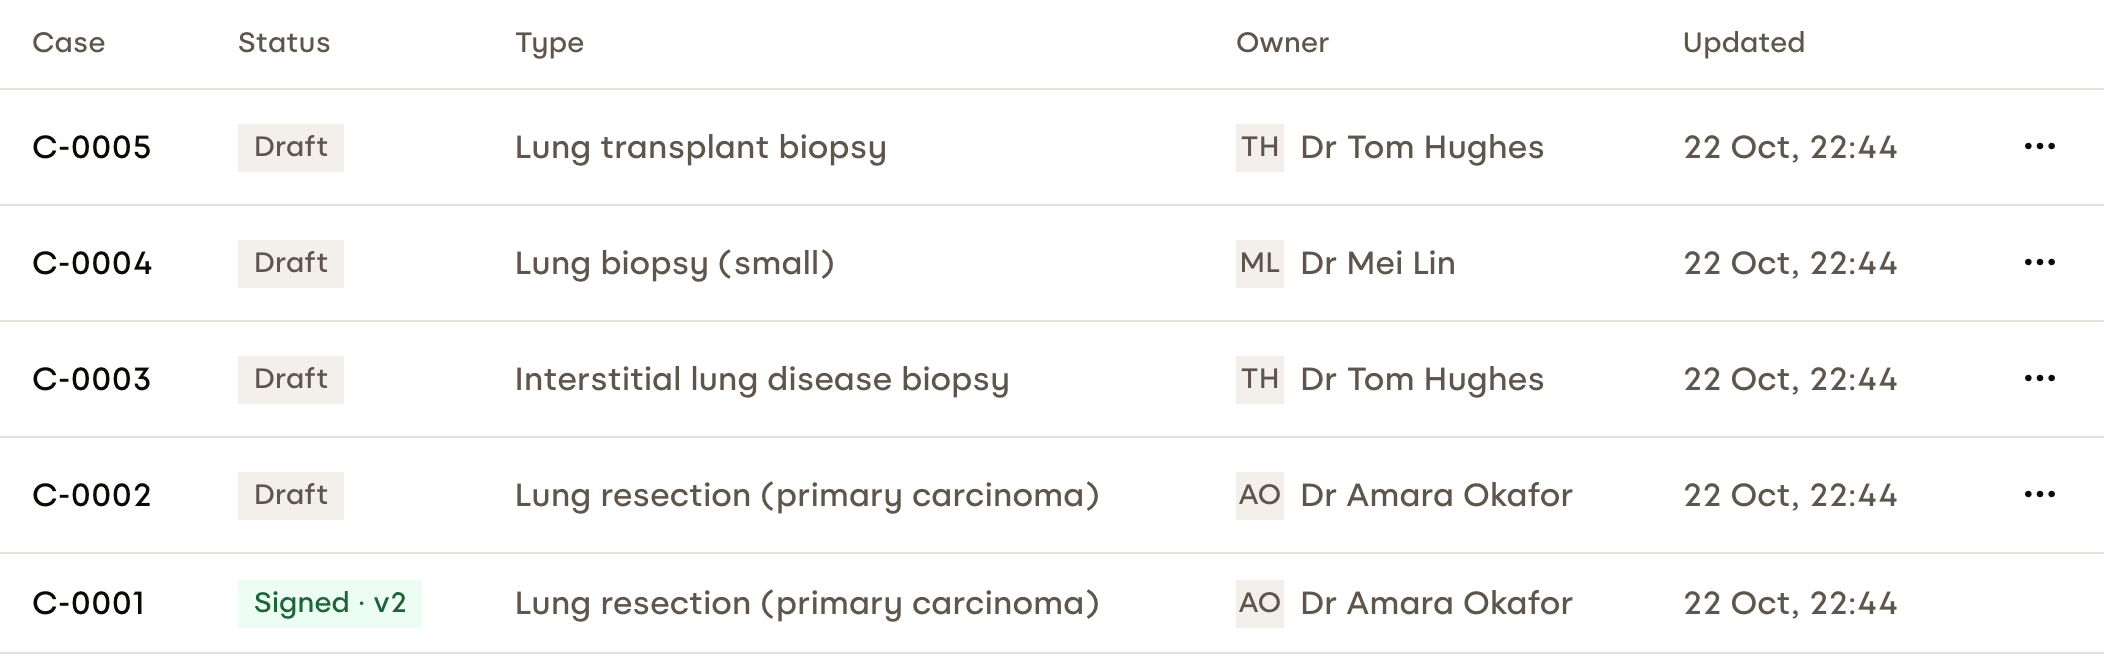
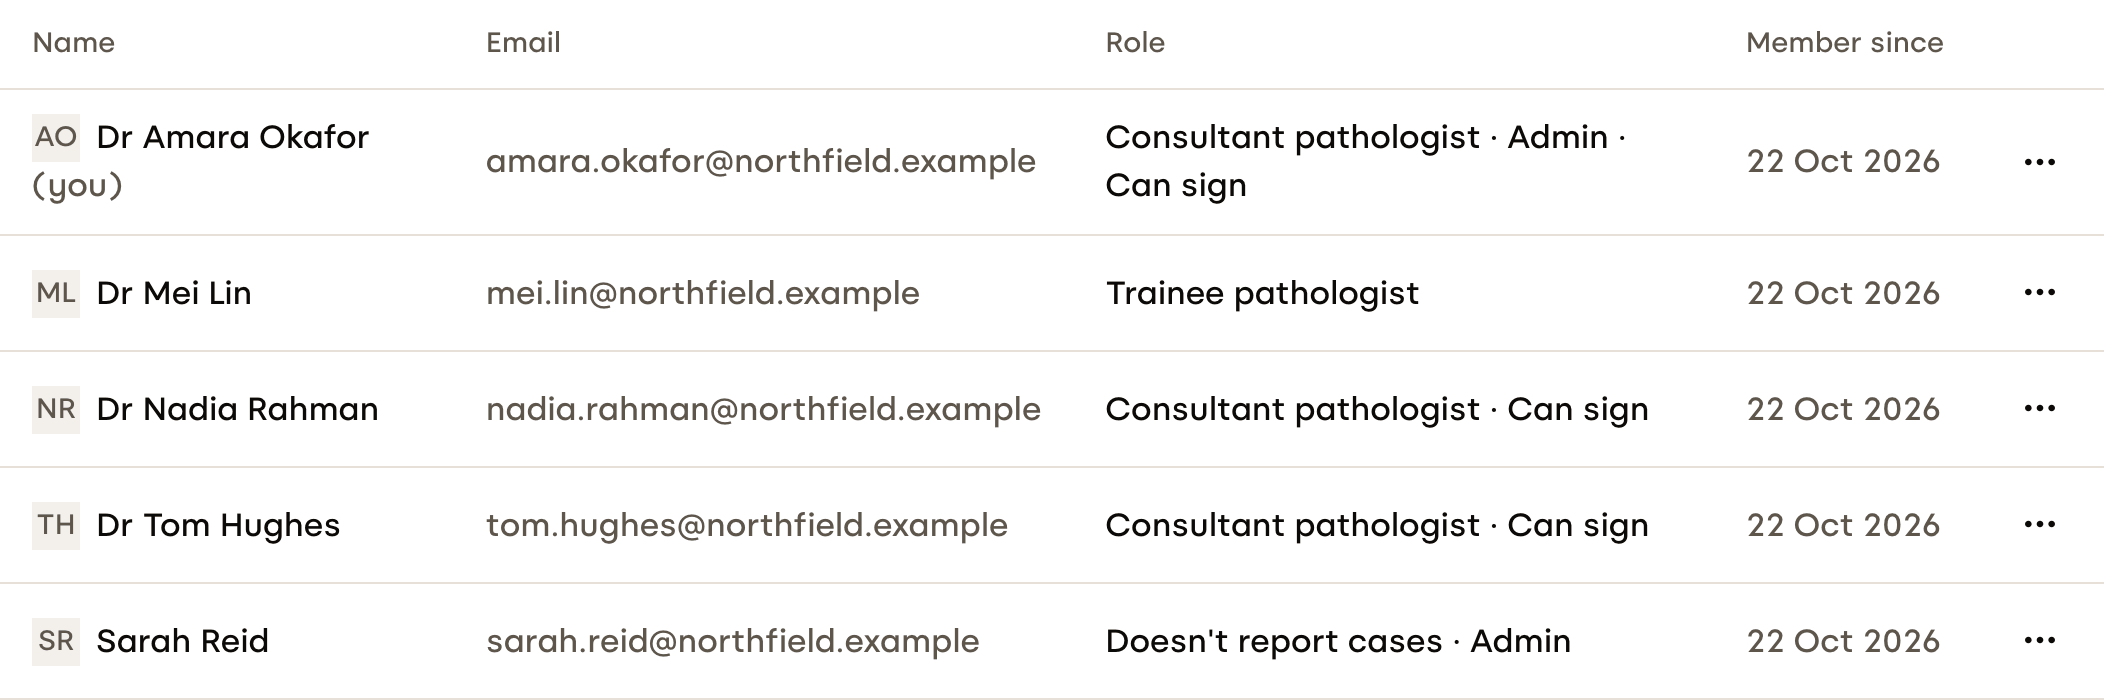
Your department, in one place
Every case, whose it is and where it stands. Every member, their role and whether they sign.
Cases, by status, type and owner.The team: consultants who sign, trainees, and staff who administer without seeing cases.
What your governance team will ask
Choose a question. The full answers are in the Trust center.
In London, encrypted
The application, its database and its file stores run in London. Sign-in is handled by Auth0, in the EU.
Each photo is encrypted (AES-256-GCM) before it leaves the server: the store only ever holds encrypted data.
Exports are encrypted too, and deleted after seven days.
Your organisation, and no one else
Every organisation is kept apart from every other.
Staff who don't report, such as management or IT, administer the team and see no cases.
A pathologist asked for a second opinion reads that one case, and can't change it.
A consultant, with permission
Each member reports as a consultant or a trainee, or doesn't report.
Signing is a separate permission that an administrator grants, only to a consultant. Nobody can grant it to themselves.
Never in place
Each signature makes a version that can't be changed, not even by the application's own database account.
An amendment carries its reason; a supplementary report is added alongside, never over.
Every action is recorded.
Only what you allow, under your contract
Off until your organisation turns it on, with its own provider and key, which Neolung keeps encrypted.
Nothing you report trains anyone else's model. No free text from other cases goes into a request: only past choices, such as a pattern picked, from your own organisation.
With patient data, only in the report types the clinical lead has approved, at the version in use.
Drafts and photos you remove, after seven days
A deleted draft, or a photo removed from a draft, is erased seven days later, and from backups 30 days after that.
A photo that is part of a signed version is never deleted.
How a department starts
A few steps for an administrator, then one decision that belongs to your governance.
Create your organisationFind your hospital in the NHS directory by its ODS code.
Verify your email domainOne DNS record, and colleagues who sign in with it are pointed to you.
Invite your teamSet each role, and grant signing to consultants.
Add your AI, if you want itYour organisation's own provider and key.
Your governance signs offOur documentation pack supports your DPIA and clinical safety review. Once your governance approves, Neolung turns patient data on for your organisation.
Ask a colleague, a consultant from the directory or a pathologist at another centre, without the case leaving Neolung. They read that case only, sign their opinion, and it stays with the case.
Ask from the case
A colleague in your department, a consultant from the directory, or a pathologist at another centre, by email. Add a question and when you'd like it by.
In your departmentThe directoryBy email
They read that case, nothing else
The report, its fields, checks and supplementary reports, its photos and CT images, without changing anything. Not your team, not your other cases. The email carries nothing about the patient.
Their opinion comes back signed
In their name, on the version of the report they read. It's kept with the case, apart from your report, and whoever asked is emailed when it's signed.
Read before you sign again
Whoever signs the report after it confirms they've read the opinion first.
For the hospital
Outside opinions only once an administrator allows them
Withdraw a request at any time; access ends at once
Access closes when they sign, or after 30 days
On patient cases, only consultants in organisations approved for patient data
Every opinion in your organisation's export
From your own practice
Turn on second opinions in your profile. Requests from the directory come to a practice of your own on Neolung, never through your hospital.
Listed once you're checked
Neolung checks your GMC specialist registration in histopathology, your identity and your indemnity. The directory never shows your email or GMC number.
Say your subspecialties, languages and turnaround. Accept or decline each request; accepting opens that case to you, read-only, for 30 days or until you sign.
Sign, and keep what you signed
Your opinion is filed with their case, in your name, and you keep what you signed. Within the 30 days you can add to it.
The directory
Ordered by name or by turnaround, never by anything else
Only consultants whose checks are all verified
An expired indemnity takes a listing down
Cases with patient data need your practice approved for them too
Neolung's AI: Turns what you dictate into the report's fields. Only what you said, never what it guesses.
You: Review every field, and change any of them.
Neolung's AI: Describes what it sees in a photo of the slide, beside the report. In some report types it may suggest a field's value, which you accept or dismiss.
You: Decide what goes into the report.
Neolung's AI: Doesn't stage, and doesn't check. The checks are fixed rules, written out and tested.
You: State the pT and pN, see each warning with the guideline behind it, and settle it.
Neolung's AI: Never signs, and never changes anything on its own.
You: Sign. Only a consultant with permission to sign can.
Off until your organisation turns it on, with its own provider. Nothing you report trains anyone else's model.
One case, start to finish
YouDictate the case as you'd tell a colleague, straight after the microscope.
Neolung's AIPuts what you said into the report's fields. Only what you said: the vascular margin wasn't, so it stays empty.
Neolung's AIReads the photo of the slide and describes it beside the report. It may suggest the histological type or the predominant pattern, never more.
Neolung's rulesCheck the case against the guidelines. Fixed rules, not the AI, and nothing changed on its own.
YouSettle each warning. Here: say the vascular margin, and restate the pT.
YouReview the report, written in the template's words, and sign it. Then paste it into the laboratory system.
Lung resection · Right upper lobeDraftSigned, version 1
Dictation
Fields
Site
Right upper lobe
Procedure
Lobectomy (lobe resection)
Histological type
Non-mucinous adenocarcinoma
Predominant pattern
Acinar
Invasive size
28 mm
Total tumour size
34 mm
Visceral pleural invasion
PL1
Bronchial resection margin
Clear
Vascular resection margin
Not statedClear
Hilar lymph nodes
Clear
Background lung findings
moderate emphysema
pT
pT1cpT2a
pN
pN0
Residual tumour (R)
R0
Photo · read by the AI, beside the report
Glands lined by crowded cells in a pink stroma.
Suggested predominant pattern: Acinar, as in your report.
Checks
Vascular resection margin is required. RCPath, ICCR
Stated pT1c is lower than the size and pleural invasion support (at least pT2a). TNM 9
Nothing left to check.
Report
MICROSCOPY
Sections from the lung show a non-mucinous adenocarcinoma with acinar (60%) along lepidic (30%) and solid (10%) patterns. The invasive component measures 28 mm and the tumour 34 mm. Tumour breaches the visceral pleura (PL1) and is away from the stapled line.
The bronchial and vascular resection margins are clear as well as the hilar lymph nodes.
Background lung shows moderate emphysema.
Lymph nodes (stations 10, 11R, 7 and 4R) show no granuloma formation or malignancy.

DIAGNOSIS
Right upper lobe resection: non-mucinous adenocarcinoma acinar predominant. pT2a (28 mm invasive component) PL1 N0 R0
Questions we're asked
Does Neolung use our cases to train AI?
No. The AI is off until your organisation turns it on, with its own provider. Nothing you report trains anyone else's model: it learns only from your own department's confirmed wording and past choices, never from another case's text.
What if the AI gets something wrong?
Every value it fills is marked as coming from the dictation or the photos, and listed for you to check. Where you said something differently later, you choose. The checks are fixed rules, not the AI, and only a consultant with permission signs.
Does it connect to our laboratory system?
It doesn't need to. The signed report goes into your laboratory system the way reports do today, by copy and paste, so nothing there changes and there's no integration to plan or pay for.
What does a pathologist need?
A browser. Dictate by voice in English, or type. Reports are written in English, in the words of the report type.
Where is our data kept?
Cases and photos are kept in London, encrypted. Sign-in is handled by Auth0, in the EU. Each organisation is kept apart from every other. The details are in the Trust center.
Can a trainee sign?
No. Trainees report; a consultant with signing permission signs. An administrator grants it to consultants, and nobody can change their own.
Can a signed report change?
Never in place. An amendment makes a new version, with its reason; a result that comes later is added alongside, as a supplementary report. Every version is kept.
Which reports does it cover?
Lung resection (primary carcinoma); lung resection, metastasis; lung biopsy (small); lung biopsy, non-neoplastic; lung resection, non-neoplastic; interstitial lung disease biopsy; lung transplant biopsy; lung explant; pleural biopsy; pneumothorax resection; lung abscess and empyema; referral opinion; respiratory cytology; and pleural fluid cytology. Each is in the explorer above.